
Fascicular block
Bifascicular block (RBBB + LPFB)
The right bundle and the left posterior fascicle are both blocked, leaving only the thin left anterior fascicle. The less common and higher-risk bifascicular block.
Last updated
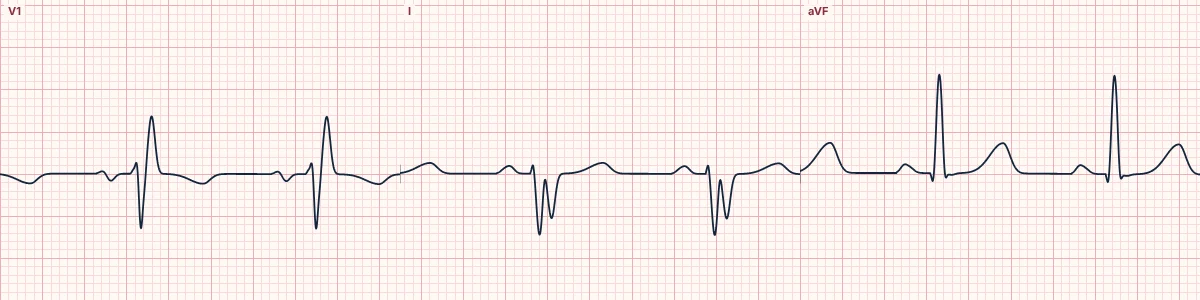
Example tracing, drawn by the lab's engine. Open the lab for a live, adjustable version.
At a glance
- QRS
- ≥ 120 ms
- V1
- rsR′ (RBBB pattern)
- I and V6
- Wide terminal S wave
- Axis
- +90° to +180° (right axis deviation)
Figures
Still images drawn by the lab's engine at 25 mm/s and 10 mm/mV, with the finding labeled. Select a figure to enlarge it.
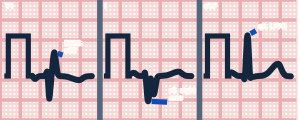
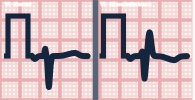
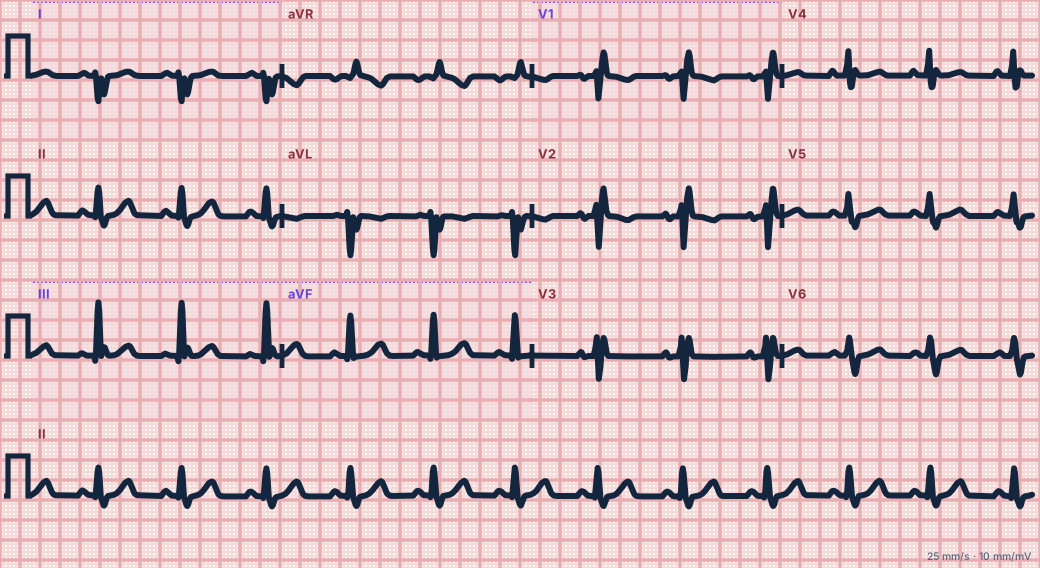
Scroll sideways to see the whole tracing, or select it to enlarge.
What the heart is doing
The impulse can descend only through the left anterior fascicle. It activates the upper lateral left ventricle first, spreads downward, and reaches the right ventricle last through muscle.
Why it looks this way
This is bifascicular block (RBBB + LPFB) because an RBBB pattern in V1 is combined with right axis deviation beyond +90°.
Why it matters
Implies widespread conduction disease and carries a higher risk of complete heart block than RBBB with LAFB. Syncope or new onset in acute infarction calls for monitoring and readiness to pace.
What to look for
- Identify RBBB in V1, then check the axis using the first 60–80 ms of the QRS.
- Lead I is mainly negative from the start and III and aVF are strongly positive.
- Exclude right ventricular hypertrophy and pulmonary embolism as the cause of the right axis.
Criteria
- QRS
- ≥ 120 ms
- V1
- rsR′ (RBBB pattern)
- I and V6
- Wide terminal S wave
- Axis
- +90° to +180° (right axis deviation)
- III and aVF
- qR complexes
Causes
- Extensive coronary artery disease
- Degenerative conduction disease
- Cardiomyopathy
- Myocarditis
- Large infarction involving the septum
Can be mistaken for
- RBBB with right ventricular hypertrophy — tall initial R in V1 and P pulmonale
- Isolated RBBB — normal axis Compare
- RBBB with acute pulmonary embolism — sinus tachycardia and T inversion in V1–V4
Advanced Down to the ion channel
What the cells are doing
Pacemaker, atrial and ventricular action potentials, in step with the tracing above, with sodium, calcium and potassium moving through their channels.
Frequently asked questions
What are the ECG criteria for bifascicular block (RBBB + LPFB)?
QRS: ≥ 120 ms. V1: rsR′ (RBBB pattern). I and V6: wide terminal S wave. Axis: +90° to +180° (right axis deviation). III and aVF: qR complexes.
How is bifascicular block (RBBB + LPFB) identified on an ECG?
This is bifascicular block (RBBB + LPFB) because an RBBB pattern in V1 is combined with right axis deviation beyond +90°.
What can bifascicular block (RBBB + LPFB) be mistaken for?
RBBB with right ventricular hypertrophy: tall initial R in V1 and P pulmonale. Isolated RBBB: normal axis. RBBB with acute pulmonary embolism: sinus tachycardia and T inversion in V1–V4.
What causes bifascicular block (RBBB + LPFB)?
Common causes: extensive coronary artery disease; degenerative conduction disease; cardiomyopathy; myocarditis; and large infarction involving the septum.
Sources
This page does not list page-specific sources yet.
Every source the site cites, with links