
Pre-excitation
WPW pattern, left-sided pathway (type A)
An accessory pathway on the left side of the heart activates part of the ventricle early, bypassing the AV node. The PR is short, with a delta wave that is upright in V1.
Last updated
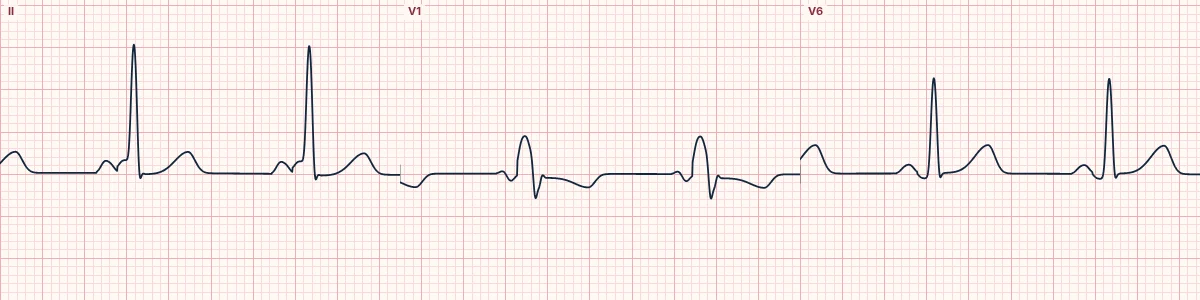
Example tracing, drawn by the lab's engine. Open the lab for a live, adjustable version.
At a glance
- PR interval
- < 120 ms
- QRS
- ≥ 110 ms with a slurred upstroke (delta wave)
- V1
- Positive (upright) delta wave; R wave prominent, often dominant
- ST–T
- Opposite to the delta wave
Figures
Still images drawn by the lab's engine at 25 mm/s and 10 mm/mV, with the finding labeled. Select a figure to enlarge it.


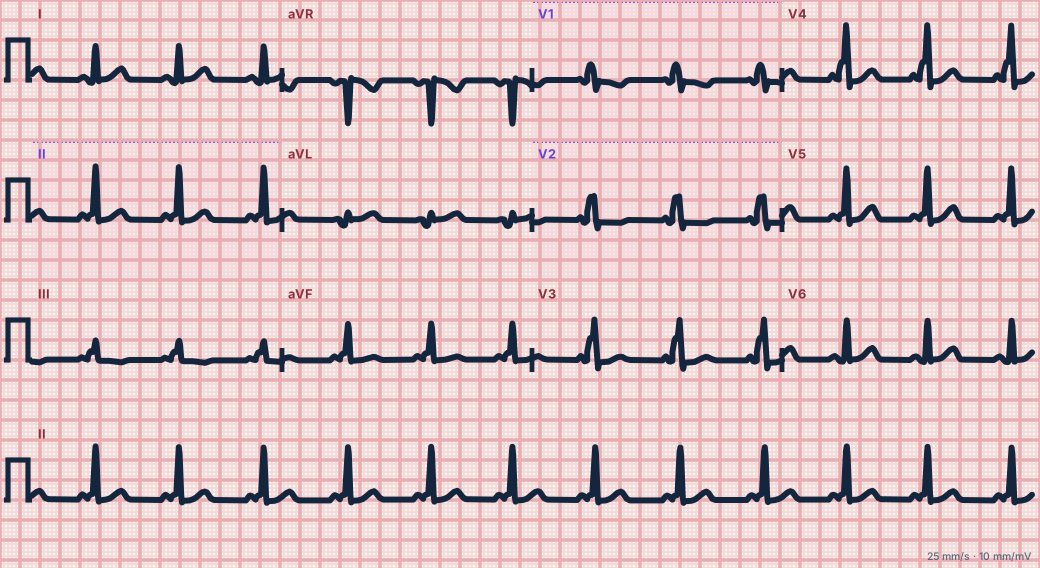
Scroll sideways to see the whole tracing, or select it to enlarge.
What the heart is doing
A strand of muscle bridges atrium and ventricle with no AV-nodal delay. Part of the left ventricle is activated early through it and fuses with the normal wavefront arriving through the AV node.
Why it looks this way
This is the WPW pattern (type A) because the PR is under 120 ms and a delta wave widens the QRS and is upright in V1.
Why it matters
The pattern alone causes no symptoms. With palpitations or syncope it is WPW syndrome: risk of AVRT and of pre-excited atrial fibrillation, which can become VF. Refer for specialist assessment.
What to look for
- The P wave runs almost straight into the QRS, with no flat PR segment.
- The first part of the QRS rises slowly, then steepens: the delta wave.
- The delta wave is upright in V1, pointing to a left-sided pathway.
Criteria
- PR interval
- < 120 ms
- QRS
- ≥ 110 ms with a slurred upstroke (delta wave)
- V1
- Positive (upright) delta wave; R wave prominent, often dominant
- ST–T
- Opposite to the delta wave
Causes
- Congenital accessory AV pathway
- Usually a structurally normal heart
- Hypertrophic cardiomyopathy (association)
- Familial forms (rare)
Can be mistaken for
- RBBB — late R′ in V1 with a normal PR Compare
- Posterior infarction or RVH — tall R in V1 without a delta wave
- Old inferior infarction — negative delta waves can imitate Q waves Compare
Advanced Down to the ion channel
What the cells are doing
Pacemaker, atrial and ventricular action potentials, in step with the tracing above, with sodium, calcium and potassium moving through their channels.
Frequently asked questions
What are the ECG criteria for WPW pattern, left-sided pathway (type A)?
PR interval: < 120 ms. QRS: ≥ 110 ms with a slurred upstroke (delta wave). V1: positive (upright) delta wave; R wave prominent, often dominant. ST–T: opposite to the delta wave.
How is WPW pattern, left-sided pathway (type A) identified on an ECG?
This is the WPW pattern (type A) because the PR is under 120 ms and a delta wave widens the QRS and is upright in V1.
What can WPW pattern, left-sided pathway (type A) be mistaken for?
RBBB: late R′ in V1 with a normal PR. Posterior infarction or RVH: tall R in V1 without a delta wave. Old inferior infarction: negative delta waves can imitate Q waves.
What causes WPW pattern, left-sided pathway (type A)?
Common causes: congenital accessory AV pathway; usually a structurally normal heart; hypertrophic cardiomyopathy (association); and familial forms (rare).
Sources
This page does not list page-specific sources yet.
Every source the site cites, with links