
Ischemia & prior infarction
Prior anterior infarction
The lasting scar of an earlier anterior wall infarct. The chest leads lose their R waves and show Q or QS waves over the damaged area.
Last updated
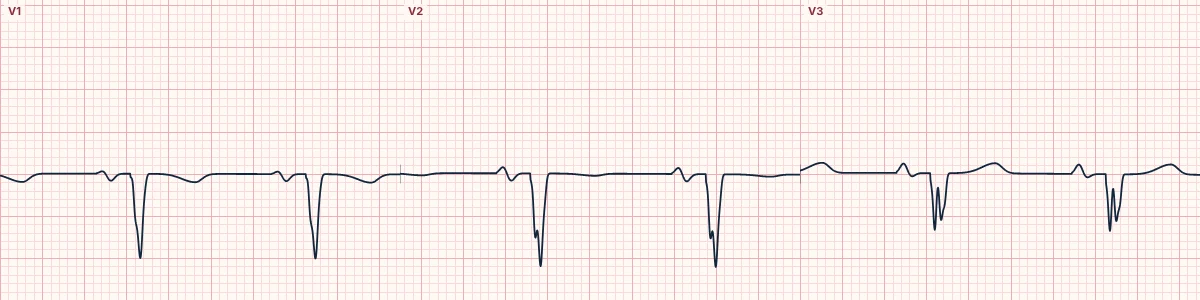
Example tracing, drawn by the lab's engine. Open the lab for a live, adjustable version.
At a glance
- Leads
- V1–V4
- QRS
- QS or Q waves with poor R-wave progression
- ST segment
- At baseline (persistent elevation suggests aneurysm)
- T waves
- May stay inverted in the same leads
Figures
Still images drawn by the lab's engine at 25 mm/s and 10 mm/mV, with the finding labeled. Select a figure to enlarge it.
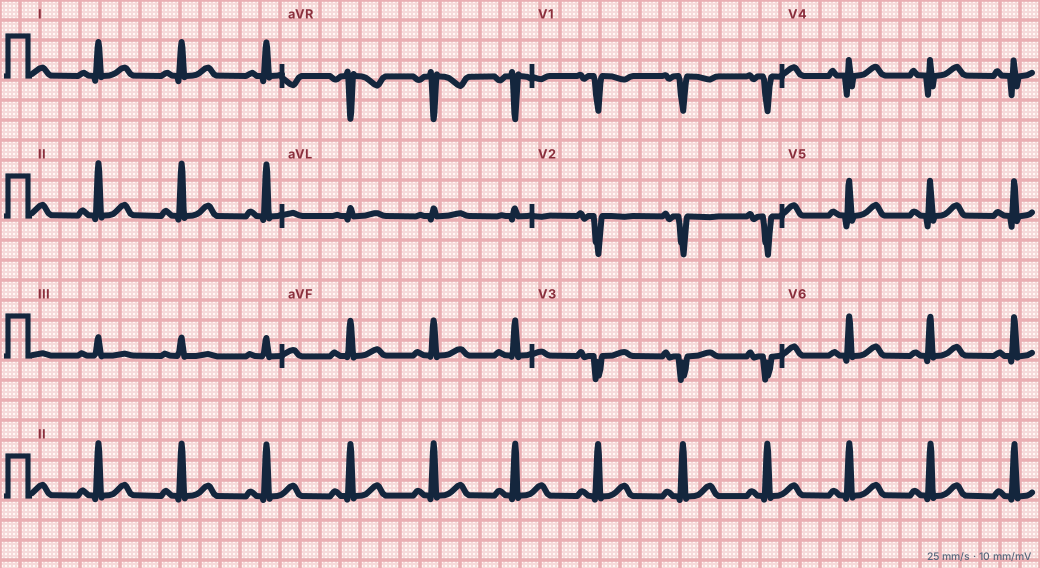
Scroll sideways to see the whole tracing, or select it to enlarge.
What the heart is doing
Scarred anterior wall produces no forward force. The chest leads over it see only depolarization moving away, toward the healthy posterior wall, so the R wave is replaced by a QS complex.
Why it looks this way
This is a prior anterior infarction because V1–V4 show Q or QS waves with poor R-wave progression and no acute ST elevation.
Why it matters
Indicates lost anterior muscle and often reduced pump function, with a long-term risk of heart failure and ventricular arrhythmias. Compare with old ECGs before calling changes new.
What to look for
- The R wave fails to grow from V1 to V4; complexes are entirely negative (QS).
- ST segments are flat, without hyperacute T waves.
- ST elevation persisting for weeks with deep Q waves suggests a left ventricular aneurysm.
Criteria
- Leads
- V1–V4
- QRS
- QS or Q waves with poor R-wave progression
- ST segment
- At baseline (persistent elevation suggests aneurysm)
- T waves
- May stay inverted in the same leads
Causes
- Previous LAD occlusion
- Silent infarction, especially with diabetes
- Chronic coronary artery disease
- Ischemic cardiomyopathy
Can be mistaken for
- LBBB — QS in V1–V3 with a wide QRS and broad lateral R waves Compare
- Chest leads placed too high — poor R progression with an inverted P in V1–V2
- Left ventricular hypertrophy — deep S waves in V1–V3 with tall lateral R waves Compare
Advanced Down to the ion channel
What the cells are doing
Pacemaker, atrial and ventricular action potentials, in step with the tracing above, with sodium, calcium and potassium moving through their channels.
Frequently asked questions
What are the ECG criteria for prior anterior infarction?
Leads: V1–V4. QRS: QS or Q waves with poor R-wave progression. ST segment: at baseline (persistent elevation suggests aneurysm). T waves: may stay inverted in the same leads.
How is prior anterior infarction identified on an ECG?
This is a prior anterior infarction because V1–V4 show Q or QS waves with poor R-wave progression and no acute ST elevation.
What can prior anterior infarction be mistaken for?
LBBB: QS in V1–V3 with a wide QRS and broad lateral R waves. Chest leads placed too high: poor R progression with an inverted P in V1–V2. Left ventricular hypertrophy: deep S waves in V1–V3 with tall lateral R waves.
What causes prior anterior infarction?
Common causes: previous LAD occlusion; silent infarction, especially with diabetes; chronic coronary artery disease; and ischemic cardiomyopathy.
Practise it in the ACLS Lab
Sources
This page does not list page-specific sources yet.
Every source the site cites, with links