
Cardiac arrest
Draft — pending owner review
Pulseless electrical activity (PEA)
An organized rhythm with no pulse
PEA is a clinical diagnosis, not an ECG rhythm: the monitor shows organized electrical activity that should produce a pulse, but the patient has none. Any rhythm except VF, pulseless VT and asystole can be PEA.
Last updated
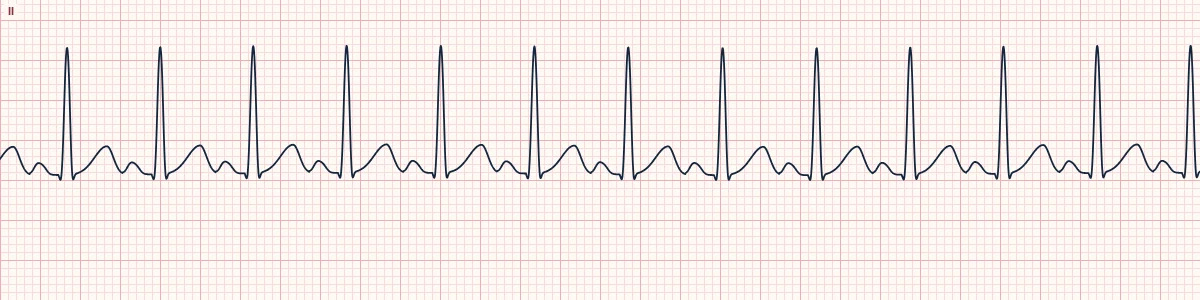
Example tracing, drawn by the lab's engine. Open the lab for a live, adjustable version.
At a glance
- H's
- Hypovolemia, hypoxia, hydrogen ion (acidosis), hypo-/hyperkalemia, hypothermia
- T's
- Tension pneumothorax, tamponade, toxins, thrombosis (pulmonary), thrombosis (coronary)
- Shockable?
- No: treat with CPR, epinephrine and the cause
- Diagnosis
- Organized rhythm on the monitor plus no pulse
Figures
Still images drawn by the lab's engine at 25 mm/s and 10 mm/mV, with the finding labeled. Select a figure to enlarge it.
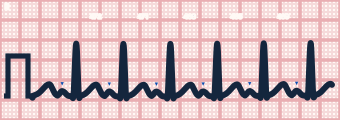
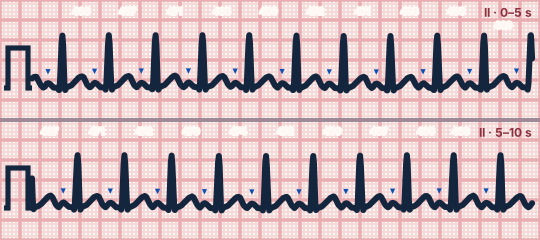
Scroll sideways to see the whole tracing, or select it to enlarge.
What you see and what you don't
The monitor might show sinus rhythm, sinus tachycardia, a junctional or idioventricular rhythm, or a wide slow rhythm. The tracing alone cannot tell you the patient is in cardiac arrest. Only the absence of a pulse (and of signs of life) makes it PEA, which is why you check the patient, not the monitor.
Why it happens
The heart is still being activated electrically, but it is not producing an output that can be felt: the ventricles are empty (bleeding, tension pneumothorax, tamponade, massive pulmonary embolism), too weak (severe acidosis, hyperkalemia, hypoxia, toxins, a large infarction) or failing as the patient dies.
The reversible causes
Survival depends on finding and treating the cause while high-quality CPR continues. The usual memory aid is the H's and T's: hypovolemia, hypoxia, hydrogen ion (acidosis), hypo- or hyperkalemia and hypothermia; tension pneumothorax, tamponade, toxins, and thrombosis in the lungs or the coronary arteries.
The teaching point
PEA is a non-shockable arrest: a shock does not help an organized rhythm without a pulse. Treat it with CPR, early epinephrine and a search for the cause. A narrow, fast PEA suggests an empty heart (hypovolemia, tamponade, tension pneumothorax, pulmonary embolism); a wide, slow PEA suggests a metabolic or toxic cause or a failing myocardium.
How to read it
- Treat the patient, not the monitor: check for a pulse whenever an organized rhythm appears during an arrest.
- Note the QRS width and rate: narrow and fast, or wide and slow, points toward different causes.
- Work through the H's and T's out loud with the team while CPR continues.
Pitfalls
- A normal-looking rhythm on the monitor does not mean the heart is pumping.
- Pulse checks should be brief: no more than 10 seconds, then resume compressions.
- Point-of-care ultrasound can show cardiac motion without a palpable pulse; follow the team's local protocol on how this changes management.
Key numbers
- H's
- Hypovolemia, hypoxia, hydrogen ion (acidosis), hypo-/hyperkalemia, hypothermia
- T's
- Tension pneumothorax, tamponade, toxins, thrombosis (pulmonary), thrombosis (coronary)
- Shockable?
- No: treat with CPR, epinephrine and the cause
- Diagnosis
- Organized rhythm on the monitor plus no pulse
Advanced Down to the ion channel
What the cells are doing
Pacemaker, atrial and ventricular action potentials, in step with the tracing above, with sodium, calcium and potassium moving through their channels.
Frequently asked questions
Pulseless electrical activity (PEA): what is the key idea?
PEA is a clinical diagnosis, not an ECG rhythm: the monitor shows organized electrical activity that should produce a pulse, but the patient has none. Any rhythm except VF, pulseless VT and asystole can be PEA.
Pulseless electrical activity (PEA): what are the key numbers?
H's: Hypovolemia, hypoxia, hydrogen ion (acidosis), hypo-/hyperkalemia, hypothermia; T's: Tension pneumothorax, tamponade, toxins, thrombosis (pulmonary), thrombosis (coronary); Shockable?: No: treat with CPR, epinephrine and the cause; Diagnosis: Organized rhythm on the monitor plus no pulse.
Pulseless electrical activity (PEA): how do you apply it to an ECG?
Treat the patient, not the monitor: check for a pulse whenever an organized rhythm appears during an arrest. Note the QRS width and rate: narrow and fast, or wide and slow, points toward different causes. Work through the H's and T's out loud with the team while CPR continues.
Pulseless electrical activity (PEA): what are the common pitfalls?
A normal-looking rhythm on the monitor does not mean the heart is pumping. Pulse checks should be brief: no more than 10 seconds, then resume compressions. Point-of-care ultrasound can show cardiac motion without a palpable pulse; follow the team's local protocol on how this changes management.
Practise it in the ACLS Lab
Sources
This page does not list page-specific sources yet.
Every source the site cites, with links