
AV blocks
Third-degree AV block, ventricular escape
No atrial impulse reaches the ventricles and the only backup is a slow ventricular pacemaker. The QRS is wide and the rate is 20–40/min.
Last updated
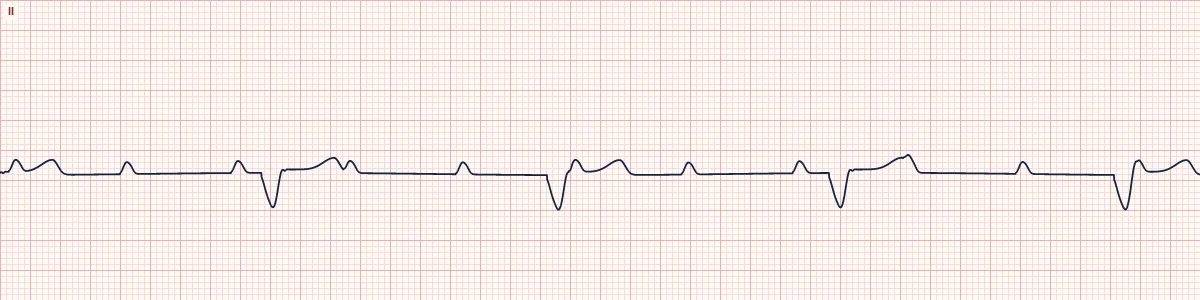
Example tracing, drawn by the lab's engine. Open the lab for a live, adjustable version.
At a glance
- Rate
- Atrial 60–100/min; ventricular 20–40/min
- Rhythm
- P–P regular and R–R regular, but unrelated
- P waves
- Normal; march through QRS and T waves
- PR interval
- Varies randomly (no true PR)
Figures
Still images drawn by the lab's engine at 25 mm/s and 10 mm/mV, with the finding labeled. Select a figure to enlarge it.
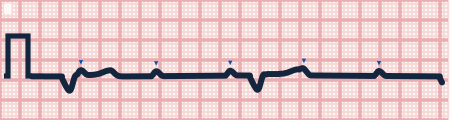
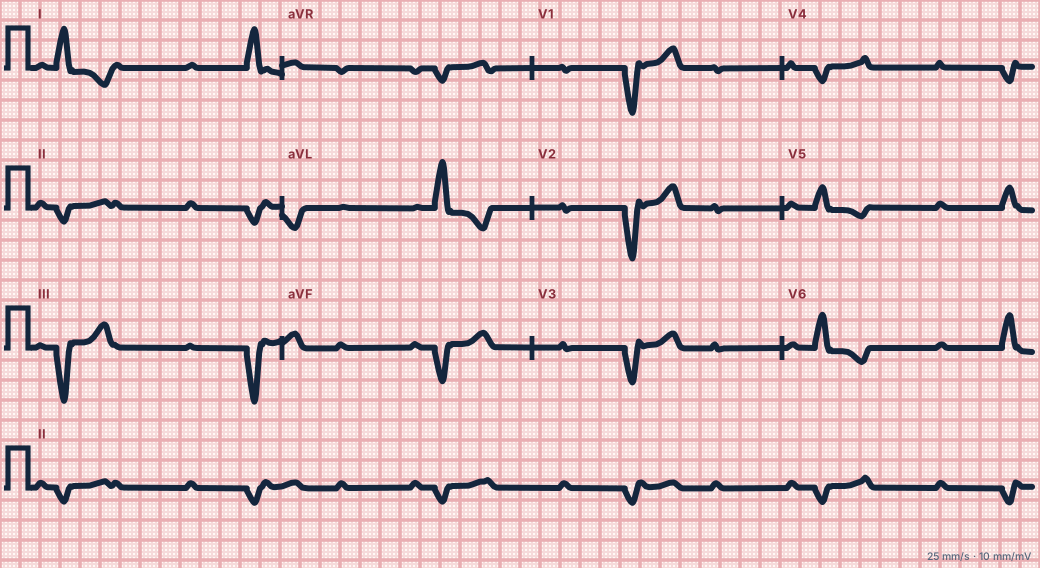
Scroll sideways to see the whole tracing, or select it to enlarge.
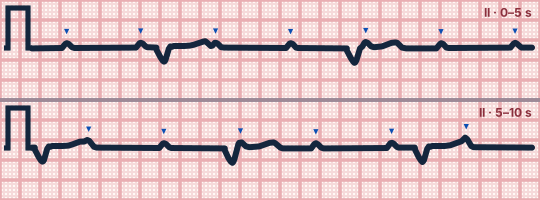
Scroll sideways to see the whole tracing, or select it to enlarge.
What the heart is doing
Conduction is interrupted below the His bundle. The sinus node still drives the atria, but the ventricles depend on a slow focus in the ventricular muscle that spreads cell to cell.
Why it looks this way
This is third-degree AV block with ventricular escape because regular P waves are unrelated to a slow, regular, wide QRS rhythm at 20–40/min.
Why it matters
An emergency. A ventricular escape is slow, unreliable and may stop without warning; atropine rarely helps. Support perfusion and move quickly to pacing; a permanent pacemaker is needed.
What to look for
- Slow, wide, regular QRS complexes with P waves scattered at a faster regular rate.
- No P wave has a consistent relationship to any QRS.
- Look for P waves deforming the T waves and ST segments.
Criteria
- Rate
- Atrial 60–100/min; ventricular 20–40/min
- Rhythm
- P–P regular and R–R regular, but unrelated
- P waves
- Normal; march through QRS and T waves
- PR interval
- Varies randomly (no true PR)
- QRS
- Wide (≥ 120 ms)
Causes
- Anterior myocardial infarction
- Degenerative fibrosis of the conduction system
- After cardiac surgery or valve procedures
- Hyperkalemia
- Drug toxicity
- Infiltrative disease
Can be mistaken for
- Third-degree block with junctional escape — narrow QRS at 40–60/min Compare
- Sinus bradycardia with bundle branch block — one P wave before each QRS at a fixed PR
- Idioventricular rhythm — no P waves at all Compare
Advanced Down to the ion channel
What the cells are doing
Pacemaker, atrial and ventricular action potentials, in step with the tracing above, with sodium, calcium and potassium moving through their channels.
Frequently asked questions
What are the ECG criteria for third-degree AV block, ventricular escape?
Rate: atrial 60–100/min; ventricular 20–40/min. Rhythm: P–P regular and R–R regular, but unrelated. P waves: normal; march through QRS and T waves. PR interval: varies randomly (no true PR). QRS: wide (≥ 120 ms).
How is third-degree AV block, ventricular escape identified on an ECG?
This is third-degree AV block with ventricular escape because regular P waves are unrelated to a slow, regular, wide QRS rhythm at 20–40/min.
What can third-degree AV block, ventricular escape be mistaken for?
Third-degree block with junctional escape: narrow QRS at 40–60/min. Sinus bradycardia with bundle branch block: one P wave before each QRS at a fixed PR. Idioventricular rhythm: no P waves at all.
What causes third-degree AV block, ventricular escape?
Common causes: anterior myocardial infarction; degenerative fibrosis of the conduction system; after cardiac surgery or valve procedures; hyperkalemia; drug toxicity; and infiltrative disease.
Practise it in the ACLS Lab
Sources
This page does not list page-specific sources yet.
Every source the site cites, with links