
Other conditions
Draft — pending owner review
Arrhythmogenic right ventricular cardiomyopathy (ARVC)
An inherited cardiomyopathy in which right ventricular muscle is replaced by fat and fibrous tissue. Its ECG signs are an epsilon wave, T inversion in V1–V3 and ventricular arrhythmias.
Last updated
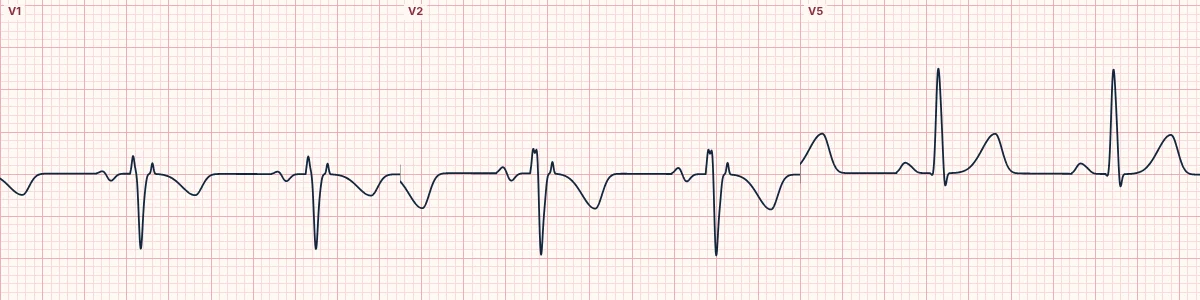
Example tracing, drawn by the lab's engine. Open the lab for a live, adjustable version.
At a glance
- T waves
- Inverted in V1–V3 (beyond age 14, without RBBB)
- Epsilon wave
- Small notch after the QRS in V1–V3
- Terminal activation
- Slow S-wave upstroke in V1–V3 (≥ 55 ms)
- Arrhythmia
- PVCs or VT with LBBB morphology
Figures
Still images drawn by the lab's engine at 25 mm/s and 10 mm/mV, with the finding labeled. Select a figure to enlarge it.
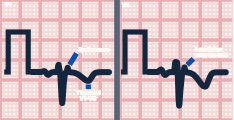
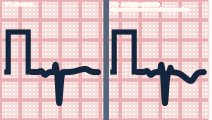
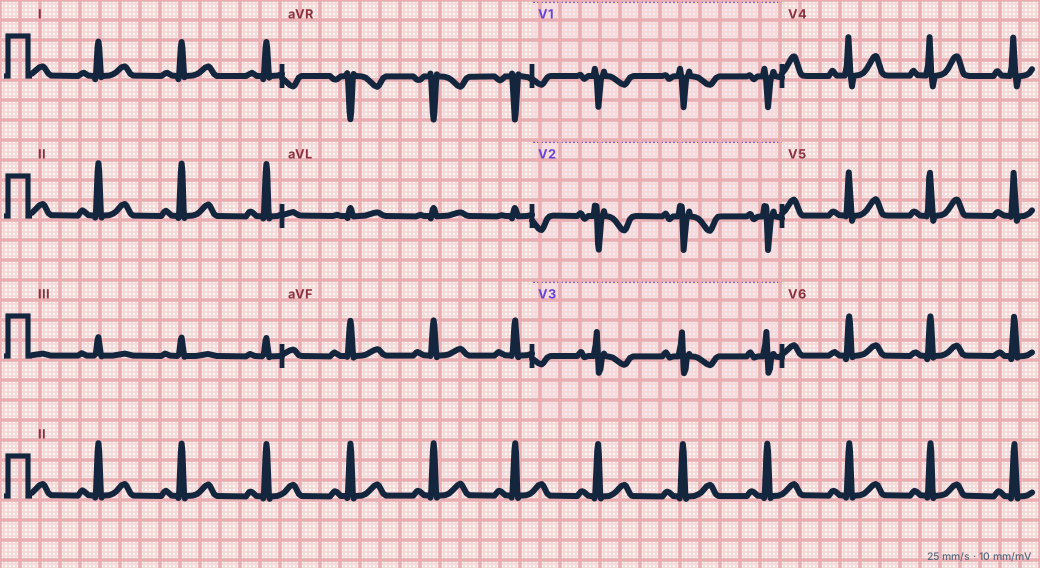
Scroll sideways to see the whole tracing, or select it to enlarge.
What the heart is doing
Fibrofatty replacement of the right ventricular free wall slows conduction there. The last part of the right ventricle activates late, writing the epsilon wave, and the scar forms circuits for re-entrant VT.
Why it looks this way
This is arrhythmogenic right ventricular cardiomyopathy because T waves are inverted in V1–V3 and a small epsilon wave follows the QRS in the right precordial leads.
Why it matters
A cause of sudden cardiac death in young people and athletes. A young patient with syncope, palpitations or LBBB-morphology VT and these ECG findings needs specialist assessment, imaging and family screening.
What to look for
- In V1–V3, look just after the QRS for a small blip before the ST segment: the epsilon wave.
- Check the T waves in V1–V3 in anyone past adolescence.
- Note the shape of any PVCs or VT: negative in V1 points to the right ventricle.
Criteria
- T waves
- Inverted in V1–V3 (beyond age 14, without RBBB)
- Epsilon wave
- Small notch after the QRS in V1–V3
- Terminal activation
- Slow S-wave upstroke in V1–V3 (≥ 55 ms)
- Arrhythmia
- PVCs or VT with LBBB morphology
- Rhythm
- Usually sinus between arrhythmias
Causes
- Desmosome gene variants (often familial)
- Endurance exercise accelerates disease expression
- Usually presents in adolescents and young adults
- Family history of sudden death
Can be mistaken for
- Brugada pattern, type 1 — coved ST elevation in V1–V2 rather than an epsilon wave Compare
- Normal infant ECG pattern — T inversion in V1–V3 is normal in children Compare
- Right bundle branch block — terminal R′ in V1 with a wide QRS Compare
Advanced Down to the ion channel
What the cells are doing
Pacemaker, atrial and ventricular action potentials, in step with the tracing above, with sodium, calcium and potassium moving through their channels.
Frequently asked questions
What are the ECG criteria for arrhythmogenic right ventricular cardiomyopathy (ARVC)?
T waves: inverted in V1–V3 (beyond age 14, without RBBB). Epsilon wave: small notch after the QRS in V1–V3. Terminal activation: slow S-wave upstroke in V1–V3 (≥ 55 ms). Arrhythmia: PVCs or VT with LBBB morphology. Rhythm: usually sinus between arrhythmias.
How is arrhythmogenic right ventricular cardiomyopathy (ARVC) identified on an ECG?
This is arrhythmogenic right ventricular cardiomyopathy because T waves are inverted in V1–V3 and a small epsilon wave follows the QRS in the right precordial leads.
What can arrhythmogenic right ventricular cardiomyopathy (ARVC) be mistaken for?
Brugada pattern, type 1: coved ST elevation in V1–V2 rather than an epsilon wave. Normal infant ECG pattern: T inversion in V1–V3 is normal in children. Right bundle branch block: terminal R′ in V1 with a wide QRS.
What causes arrhythmogenic right ventricular cardiomyopathy (ARVC)?
Common causes: desmosome gene variants (often familial); endurance exercise accelerates disease expression; usually presents in adolescents and young adults; and family history of sudden death.
Sources
This page does not list page-specific sources yet.
Every source the site cites, with links