
Junctional & SVT
Antidromic AVRT
A re-entrant tachycardia that runs down an accessory pathway and back up the AV node. The ventricles are fully pre-excited, so the QRS is wide.
Last updated
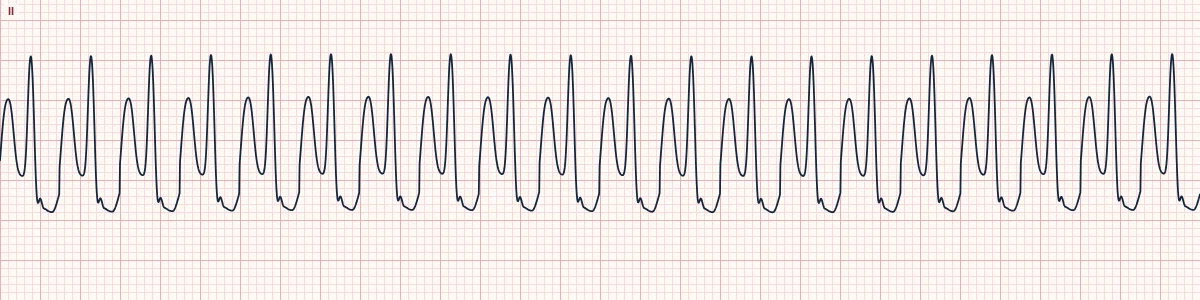
Example tracing, drawn by the lab's engine. Open the lab for a live, adjustable version.
At a glance
- Rate
- 150–250/min
- Rhythm
- Perfectly regular
- P waves
- Retrograde, usually hidden in the ST–T
- QRS
- Wide (≥ 120 ms) with a slurred upstroke
Figures
Still images drawn by the lab's engine at 25 mm/s and 10 mm/mV, with the finding labeled. Select a figure to enlarge it.

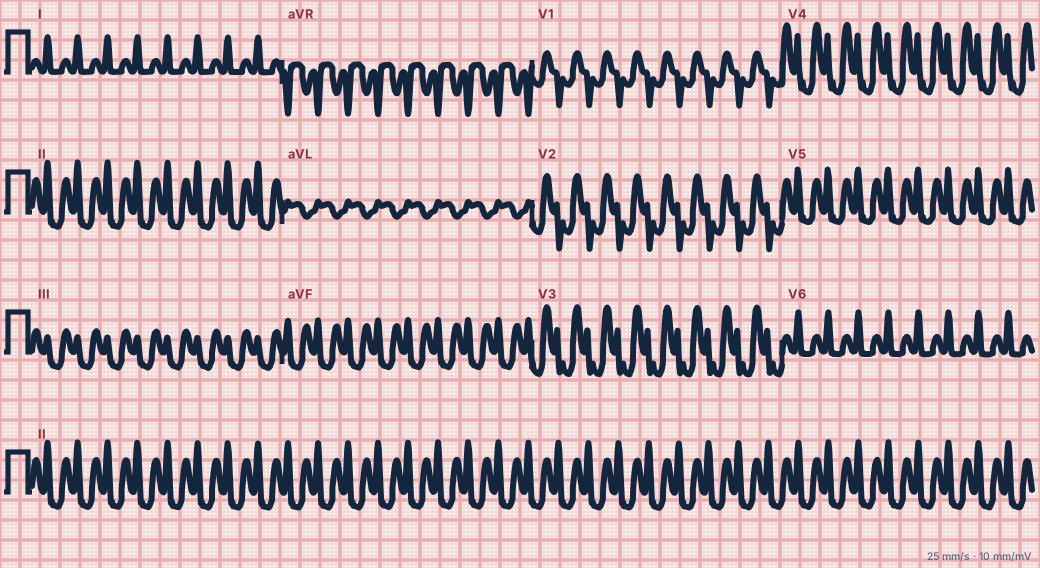
Scroll sideways to see the whole tracing, or select it to enlarge.
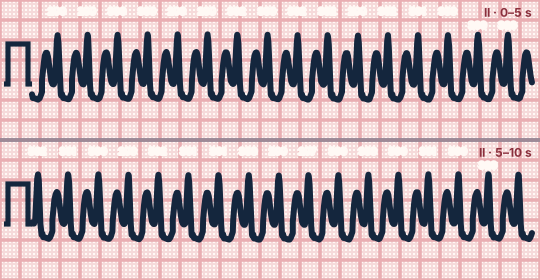
Scroll sideways to see the whole tracing, or select it to enlarge.
What the heart is doing
The impulse reaches the ventricles through the accessory pathway, spreading slowly cell to cell, then returns to the atria through the His bundle and AV node to complete the circuit.
Why it looks this way
This is antidromic AVRT because the regular tachycardia has wide, fully pre-excited QRS complexes with a slurred onset and constant shape.
Why it matters
Treat as ventricular tachycardia if there is any doubt. Unstable patients need immediate synchronized cardioversion; stable patients need expert-guided drug choice, since AV nodal blockers can be hazardous.
What to look for
- A regular wide tachycardia whose QRS begins with a slow, slurred delta-like upstroke.
- Compare with a sinus ECG if available: the QRS looks like a magnified version of the pre-excited beat.
- It cannot be reliably told from VT on the strip alone.
Criteria
- Rate
- 150–250/min
- Rhythm
- Perfectly regular
- P waves
- Retrograde, usually hidden in the ST–T
- QRS
- Wide (≥ 120 ms) with a slurred upstroke
- Morphology
- Constant; an exaggerated delta-wave pattern
Causes
- WPW with a manifest accessory pathway
- Triggered by a PAC or PVC
- Multiple accessory pathways
- Ebstein anomaly
Can be mistaken for
- Monomorphic VT — look for AV dissociation, fusion or capture beats Compare
- SVT with bundle branch block — typical RBBB or LBBB shape with a sharp onset
- Pre-excited atrial fibrillation — irregular, with changing QRS width Compare
Advanced Down to the ion channel
What the cells are doing
Pacemaker, atrial and ventricular action potentials, in step with the tracing above, with sodium, calcium and potassium moving through their channels.
Frequently asked questions
What are the ECG criteria for antidromic AVRT?
Rate: 150–250/min. Rhythm: perfectly regular. P waves: retrograde, usually hidden in the ST–T. QRS: wide (≥ 120 ms) with a slurred upstroke. Morphology: constant; an exaggerated delta-wave pattern.
How is antidromic AVRT identified on an ECG?
This is antidromic AVRT because the regular tachycardia has wide, fully pre-excited QRS complexes with a slurred onset and constant shape.
What can antidromic AVRT be mistaken for?
Monomorphic VT: look for AV dissociation, fusion or capture beats. SVT with bundle branch block: typical RBBB or LBBB shape with a sharp onset. Pre-excited atrial fibrillation: irregular, with changing QRS width.
What causes antidromic AVRT?
Common causes: WPW with a manifest accessory pathway; triggered by a PAC or PVC; multiple accessory pathways; and ebstein anomaly.
Sources
This page does not list page-specific sources yet.
Every source the site cites, with links